Radiology reader support in Nigeria: coverage, clinical responsibility and quality

What does radiology reader support in Nigeria involve?
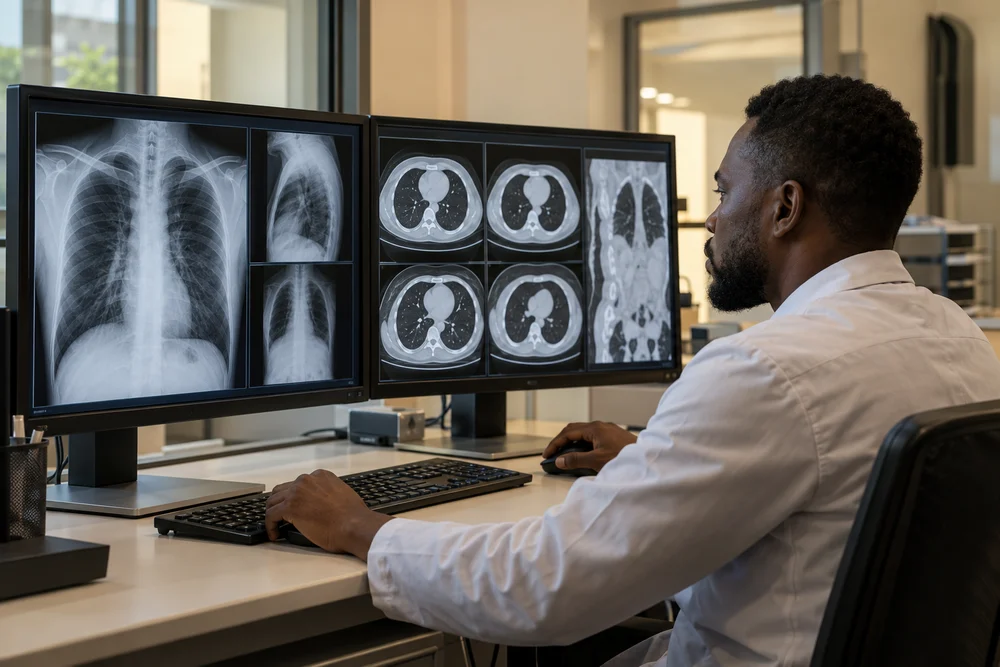
Radiology reader support concerns the people and workflow needed to produce, communicate and review imaging reports within an agreed clinical service. Discuss the reporting gap with Franance so the arrangement addresses your actual modality mix, coverage and responsibilities.
A facility may need help defining routine reporting cover, a temporary gap, a specific backlog or the workflow between image acquisition and an authorised report. Those requirements should be separated. State whether the problem is access to an appropriate reporting professional, incomplete study information, an IT interface or a coordination issue; different problems need different scopes.
Begin with a service brief rather than sending a collection of patient studies. Identify the organisation, clinical lead, modalities, approximate volumes and the reporting environment. This allows the next discussion to focus on coverage and responsibility. A general enquiry is not an instruction to interpret an examination and does not create an emergency reporting service.
How should a facility define its reporting coverage?
Specify modalities, examination types, approximate workload, required hours and the reporting expertise needed. Separate routine work, urgent work and backlog activity so the proposed cover can be reviewed against real demand rather than one undifferentiated study total.
Describe the pattern of work across the day or week and any predictable peaks. State whether studies arrive continuously or in scheduled batches, and whether prior examinations and relevant clinical information can be made available through the agreed workflow. Identify complex or specialist examinations that may need a different reporting arrangement rather than assuming one reader covers every possible study.
Agree how work is accepted into the service and what happens when a study falls outside scope. Define any volume assumptions and the route for discussing additional work. Coverage hours, reporting turnaround and availability must be confirmed in the actual proposal; they should not be inferred from a website description or from a different facility’s arrangement.
What should be checked about radiology reporting professionals?
Confirm the identity, relevant professional status, current registration and competence of the professionals responsible for reporting. The facility’s clinical leadership should approve the reporting scope and any credential-verification requirements before the service starts.
Ask which named professional or accountable reporting organisation issues the report and how the report author is identified. Review experience relevant to the agreed modality and study mix. Where professional status is claimed in Nigeria, use the relevant verification route; the Medical and Dental Council of Nigeria provides a doctor-status confirmation service. Keep evidence of the review with the service records.
Do not treat secure software access as permission to provide clinical interpretation. The technical team can configure systems and access, but clinical reporting responsibility belongs to appropriately authorised professionals within the agreed service. A staffing or IT proposal should make that distinction clear, including any exclusions, supervision arrangements or subspecialty escalation.
What information should be available to the reader?
Agree a study-readiness checklist covering the correct examination, patient and request identifiers, relevant clinical question, image completeness and any required prior-study access. The facility and reporting team should define how missing or inconsistent information is resolved.
A reporting queue is more useful when each case can be matched to the correct request and clinical context. Identify the team responsible for acquisition completeness and the contact a reader can approach for clarification. Keep corrections traceable instead of relying on informal messages that do not connect back to the examination and its authorised record.
Set a process for studies that cannot be reported as submitted. That may involve a documented clarification request, additional information or escalation to the facility’s responsible clinician. The service agreement should explain how such cases are tracked and how they affect workflow assumptions. This is an operating-process decision for the participating clinical teams, not a generic promise that every received image can immediately produce a final report.
How should reports and important findings reach the clinical team?
Define where authorised reports are delivered, how the responsible clinical team receives them and how urgent or unexpected findings are escalated. A report being uploaded to a system is different from an agreed communication or acknowledgement process.
Name the report destination and the clinical contacts for the relevant coverage periods. Agree how preliminary reports, final reports and later amendments are distinguished and reconciled. Where an examination needs prompt clinical attention, the responsible clinicians should determine the escalation pathway, communication method and record of the contact rather than relying solely on a routine inbox.
Include practical failure cases in the workflow discussion: an unavailable contact, an unread message, a report correction or an interrupted system connection. State who follows up unresolved communication and how it is handed over between shifts. Clear responsibilities support continuity without inventing a universal turnaround time or suggesting that a website enquiry can substitute for a facility’s emergency pathway.
How should radiology reader support quality be reviewed?
Agree clinical quality-review, feedback and discrepancy processes alongside operational measures such as workload and turnaround. The responsible clinical leadership should set the review method, ownership and response to findings for the actual reporting service.
Separate report-quality review from a simple count of completed cases. Define how feedback reaches the reporting professional, how amendments are authorised and how learning or corrective actions are recorded. A useful agreement also identifies the route for complaints or concerns and who may review the original images and relevant clinical context under the agreed access arrangements.
Review the service at an agreed interval with the people responsible for clinical work and operations. Look for recurring information gaps, communication problems and work that falls outside the agreed scope. The purpose is to improve a defined service, not to replace professional judgement with a single numerical performance target or a claim that all reports are free of disagreement.
How do PACS, RIS and access arrangements fit into reader support?
The reporting arrangement needs an agreed technical route for study access, reporting and record reconciliation. Confirm the existing systems, account permissions, support contacts and data responsibilities before clinical work is introduced into a new workflow.
Identify the current PACS, RIS or other reporting environment and who controls it. Define which actions a reader needs to perform, how individual access is authorised and how access is removed when an engagement ends. If technical integration is required, scope it separately with the system owners rather than assuming a reader-support agreement automatically includes a complete IT implementation.
Patient information should move only through the channels approved for the service. Agree the organisations’ respective responsibilities for access, retention, incident handling and any onward transfer, with the appropriate privacy and clinical reviewers involved. The initial Franance enquiry should contain service-level information; patient images, names and medical records are not needed to explain the coverage requirement.
How do I request a radiology reader support proposal?
Contact Franance with a service-level brief covering the facility, modalities, workload, hours, current systems and responsible clinical contact. State the reporting problem you need to solve and which arrangements are already in place.
Useful supporting information includes the division between routine and other work, required subspecialty scope, how reports are currently issued and the main operational constraints. If the request concerns leave cover or a backlog, define the period and expected volume rather than describing it as an unlimited reporting requirement. Do not include patient cases in the general enquiry form.
The next proposal should identify the intended operating model, clinical and technical responsibilities, credential review, quality arrangements, access process and commercial basis. Franance can help clarify those interfaces so the facility can assess a concrete service brief. Reporting should begin only through the agreed controlled process with the appropriate responsible professionals identified.
Common questions about radiology reader support in Nigeria
Is radiology reader support the same as PACS installation?
No. Reader support concerns reporting coverage and workflow; PACS installation concerns a technical system. They may be connected, but clinical interpretation, account access, image transfer and IT support need separately identified responsibilities. Franance can help scope the reporting and technical requirements together without treating them as interchangeable.
Can I request temporary cover or backlog support?
Yes, describe the period, modalities, study mix and approximate volumes in a service enquiry. The reporting professionals, scope, hours, turnaround and quality arrangements must be confirmed for the proposed engagement. A request does not automatically establish reader availability or an emergency reporting commitment.
Should I send patient images with my first enquiry?
No. Start with organisation, workload, coverage and system information. Patient studies should be transferred only after the service’s clinical responsibility, authorised access, privacy arrangements and technical workflow are agreed. The public website form is for a service brief, not clinical image submission.
Who is responsible for the imaging report?
The proposal should identify the appropriately authorised reporting professional or accountable reporting organisation and the facility’s clinical responsibilities. Confirm how the author is identified, how credentials are reviewed and how feedback or an amendment is handled. Technical access alone does not establish clinical reporting authority.
How can I discuss radiology reader support with Franance?
Use the on-page enquiry or callback control with your facility, modalities, coverage gap, current reporting system and clinical contact. Franance will follow up to clarify the proposed service and its interfaces. Do not include patient identifiers or use this enquiry route for an urgent clinical case.
Build reporting support around your clinical service.
Contact Franance with the coverage gap and reporting workflow you need to address. We will help clarify the brief, responsible parties and next discussion without asking for patient studies in the initial enquiry.
Contact Franance